고혈압과 퇴행성관절염 — 2026 Science 연구, 관절 치료비를 바꿀까Hypertension and osteoarthritis: Can a 2026 Science study change the cost of care?
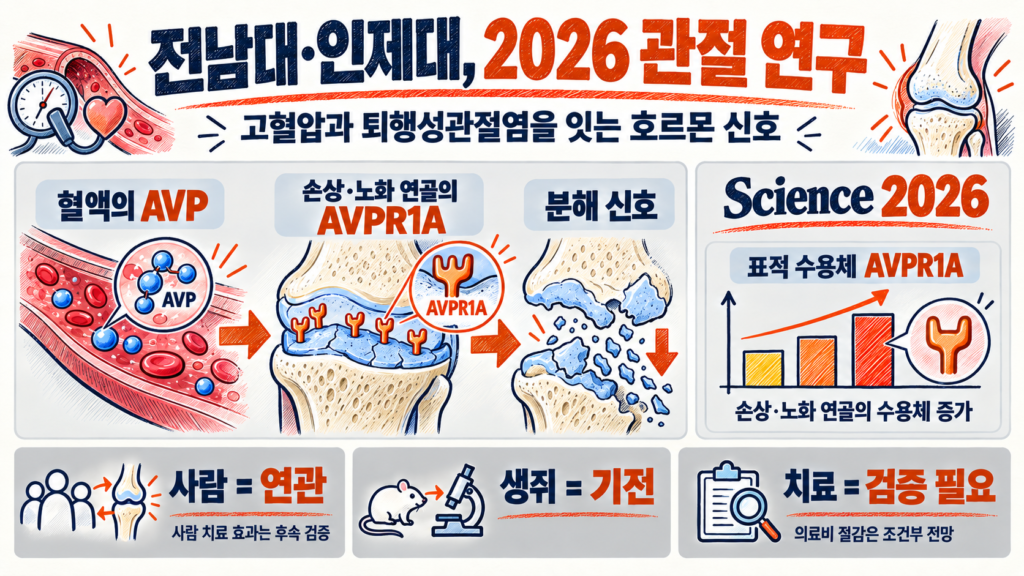
전남대학교 류제황 교수와 인제대학교 전장수 석좌교수 공동연구팀이 고혈압과 퇴행성관절염을 잇는 호르몬 신호를 제시했습니다. 2026년 10월 1일 미국 현지에서 발표된 Science 연구의 핵심은 손상되거나 노화된 연골이 혈중 바소프레신에 민감해진다는 점입니다. 이 발견이 치료제와 의료비 절감으로 이어지려면 무엇을 더 입증해야 할까요? 출처: 전남대 공식 발표
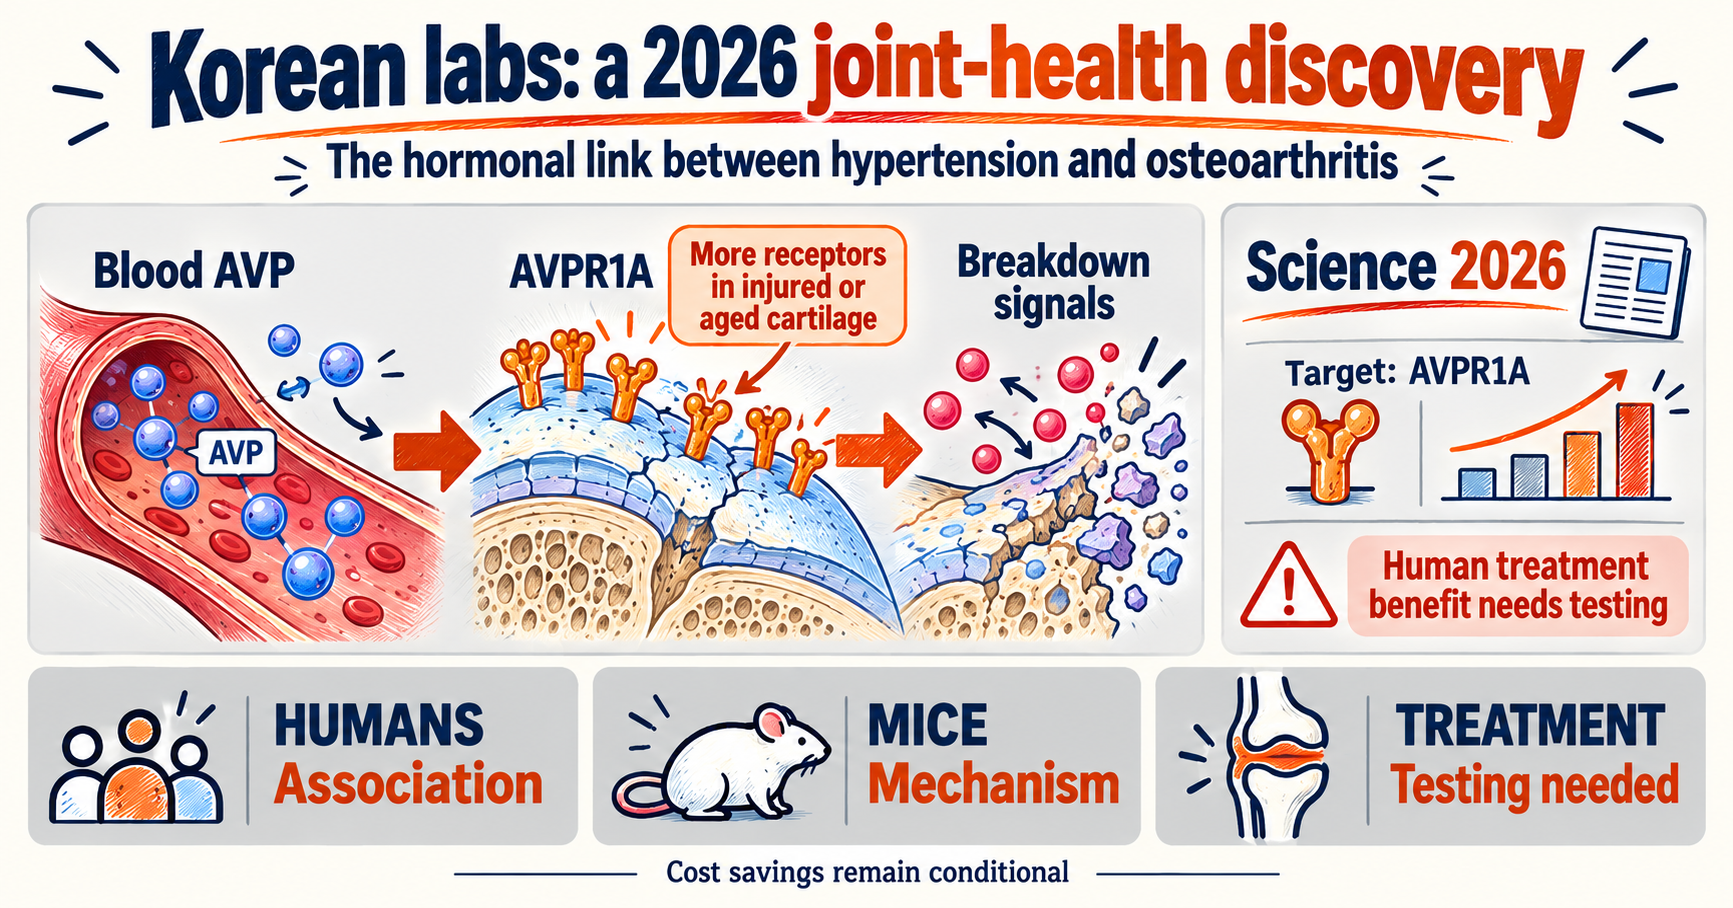
Je-Hwang Ryu of Chonnam National University and Jang-Soo Chun of Inje University have identified a hormonal link between hypertension and osteoarthritis. Their Science study, released on October 1, 2026 in the United States, describes how injured or aged cartilage becomes responsive to circulating vasopressin. The economic question is what must happen before that discovery can lower the cost of care. Source: 전남대 공식 발표
병원에서 혈압을 재고 무릎 사진을 찍는 일은 서로 다른 진료처럼 느껴집니다. 하지만 몸 안에서는 혈액을 타고 이동하는 신호가 두 부위를 연결할 수 있습니다. 그렇다고 혈압약을 잘 챙겨 먹으면 관절염이 낫는다는 뜻은 아닙니다. 이번 성과는 사람에게 치료 효과를 입증한 임상시험이 아니라, 동물실험으로 경로를 확인한 단계입니다.
류제황·전장수 연구팀은 누구인가
류제황·전장수 교수가 공동 교신저자로 연구를 이끌었고, 전남대 김수진 박사후연구원과 김효은 연구원이 공동 제1저자로 참여했습니다. 대학 발표는 두 연구자가 연구를 수행했다고 밝히지만, 각 실험을 누가 맡았는지까지 구분하지는 않습니다. 출처: 연구진 명단
두 책임연구자의 관심은 오래전부터 연골 바깥의 대사 문제와 이어져 있었습니다. 2019년 Nature 논문에서도 류제황·전장수 교수는 공동 교신저자로 콜레스테롤 대사가 골관절염을 조절하는 경로를 다뤘습니다. 이번 연구는 그 질문을 혈압과 신경내분비 신호로 넓혔습니다. 신경내분비란 신경계가 만든 호르몬이 혈액을 통해 다른 조직에 영향을 주는 방식입니다. 출처: Nature 2019 선행 연구
고혈압과 퇴행성관절염, ‘닳아서 생긴다’는 설명에 더해진 것
바소프레신, 줄여서 AVP는 몸의 수분과 혈압 조절에 관여하는 호르몬입니다. AVPR1A는 세포가 이 호르몬의 신호를 받아들이는 수용체입니다. 류제황·전장수 연구진이 주목한 것은 호르몬의 양과 함께, 연골 쪽에서 그 신호를 얼마나 잘 받아들이느냐였습니다.
논문 초록에 따르면, 골관절염에 취약해진 연골세포에서는 AVPR1A가 증가했습니다. 이 세포들이 고혈압과 관련된 순환 AVP에 반응하면서 연골을 분해하는 신호는 커지고, 만드는 쪽의 조절 신호는 약해졌습니다. 연구진은 유전자 발현 분석과 유전자 억제 실험을 통해 NR4A3라는 전사인자도 찾아냈습니다. 전사인자는 세포가 어떤 유전자를 작동시킬지 조절하는 단백질입니다. 출처: Science 초록 재수록
여기서 중요한 조건이 있습니다. 정상 연골의 수용체는 적고, 손상·노화된 연골에서는 늘어난다는 점입니다. 혈압이 높으면 누구나 정상 연골부터 망가진다고 일반화할 수 없습니다. 관절의 기존 상태와 전신의 신호가 함께 작용한다는 설명입니다. 출처: 연골 상태에 따른 차이
-
1
혈중 AVP
고혈압과 관련된 호르몬 신호
-
2
연골의 AVPR1A
손상·노화로 수용체 증가
-
3
분해 신호 증가
NR4A3 등 하위 조절 경로
-
4
퇴행 가속
취약한 관절의 악화 경로
과학적으로 새로워진 질문은 어느 관절이 얼마나 닳았느냐에서 한 걸음 더 나아갑니다. 어떤 세포가 왜 같은 호르몬에 더 강하게 반응하느냐를 묻게 됩니다. 몸무게와 사용량이 중요하다는 기존 설명을 버리는 대신, 질환의 진행 속도를 바꿀 수 있는 분자 표적을 더한 셈입니다.
사람의 연관성과 생쥐의 인과는 어디서 갈리나
김수진·김효은 공동 제1저자가 참여한 연구는 국민건강영양조사 자료에서 출발한 연관성을 생쥐 실험으로 이어 갔습니다. 공식 발표에 따르면 서로 다른 두 종류의 고혈압 모델에서 골관절염 악화를 확인했습니다. 사람에게서 두 병이 함께 나타나는 관찰과, 실험 조건을 바꿔 악화 경로를 확인하는 작업은 서로 다른 증거입니다. 출처: 과기정통부·KDI 연구 요약
사람 자료에는 나이, 체중, 활동량, 약물 사용 같은 요인이 함께 얽힐 수 있습니다. 통계적으로 조정해도 남는 차이가 있을 수 있으므로, 관찰자료만으로 혈압을 낮추면 관절 손상이 줄어든다고 결론 낼 수 없습니다. 생쥐에서는 AVPR1A 유전자를 없애거나 약물로 막았을 때 악화가 억제돼 표적의 인과적 역할을 뒷받침했습니다. 다만 그 결과가 사람의 장기 치료 효과를 대신하지는 않습니다. 출처: Science 초록의 실험 결과
사람 관찰자료
고혈압·골관절염 연관
확인
한계 · 혈압 치료의 관절 효과는 미확인
생쥐 개입실험
수용체 결손·억제로 악화 억제
확인
한계 · 사람의 장기 효능으로 일반화 불가
자료 확인 범위도 분명히 해둡니다. 이 글은 출판사 원문 접근 제한으로 논문 초록 재수록과 전남대·정부 공식 발표를 대조해 작성했습니다. 전문과 보충자료의 표본수·세부 투여 조건·효과 크기를 직접 확인하지 못했으므로, 개선율이나 사람의 위험 증가 배수는 제시하지 않습니다.
렐코밥탄은 처방약이 아니라 신약 개발의 출발점입니다
류제황 연구진은 AVPR1A 억제 물질인 렐코밥탄(relcovaptan)을 사용한 동물실험에서도 연골 손상이 줄었다고 보고했습니다. 새로운 표적을 발견하는 데서 멈추지 않고, 약물로 건드릴 수 있는지까지 시험했다는 의미입니다. 하지만 이번 발표만으로 렐코밥탄을 승인된 골관절염 치료제나 바로 바꿔 먹을 혈압약으로 소개할 수는 없습니다. 출처: 렐코밥탄 동물실험
개발사가 이 결과를 이어받는다면 우선 약물이 사람 관절에 충분히 도달하는지, 효과가 얼마나 오래가는지 확인해야 합니다. 전신 투여와 관절 내 투여는 노출 범위와 반복 투약 부담이 다릅니다. 고령 환자는 여러 약을 함께 쓰는 경우도 있어 장기 안전성 평가가 중요해집니다. 이는 이번 논문이 해결한 결과가 아니라, 후속 개발에서 검증할 과제입니다.
연구비를 줄일 가능성은 환자 선별에서 먼저 생길 수 있습니다. 고혈압이 있고 해당 신호가 활성화된 환자를 구별할 수 있다면, 반응 가능성이 낮은 사람까지 넓게 모집하는 시행착오를 줄일 여지가 있습니다. 반대로 신호를 확인하는 검사에 비용이 많이 들거나 예측력이 낮으면 개발비가 더 들 수 있습니다. 혈압 수치 하나만으로 약효를 예측하는 검사는 아직 아닙니다.
연골 사진이 좋아져도 치료비가 바로 줄지는 않습니다
류제황·전장수 교수팀의 표적을 경제적으로 평가할 때 참고할 만한 선례가 있습니다. Marc Hochberg와 Merck KGaA·EMD Serono 연구진 등이 참여한 FORWARD 임상시험입니다. 2019년 JAMA 보고에서 스프리퍼민(sprifermin)의 높은 용량군은 연골 두께에 효과를 보였지만, 전체 분석 집단의 통증·기능 등 증상 지표는 위약보다 유의하게 좋아지지 않았습니다. 다른 약의 과거 결과이며, 렐코밥탄의 실패를 예측하는 자료는 아닙니다. 출처: JAMA FORWARD 임상
이 사례가 보여주는 사업화 과제는 선명합니다. 영상에서 연골이 보존되는 결과, 환자가 덜 아프고 더 잘 걷는 결과, 수술을 늦추는 결과를 따로 측정해야 합니다. 보험자에게 설득력 있는 가치는 세 결과가 실제 생활의 편익으로 이어질 때 커집니다. 약값을 받기 위해 필요한 임상 증거와 실험실에서 표적을 검증하는 증거의 거리는 꽤 깁니다.
WHO가 제시한 세계 골관절염 환자는 2019년 기준 약 5억2800만 명입니다. 이는 부담의 크기를 보여줄 뿐, 새 약의 고객 수는 아닙니다. 그중 해당 기전이 중요한 환자, 치료가 도움이 되는 질환 단계, 안전하게 투약할 수 있는 사람을 가려야 합니다. 세계 유병인구에 가상의 약값을 곱해 매출을 계산하면 가장 중요한 조건들이 빠집니다. 출처: WHO·2019년 기준
한국 의료산업에서 돈이 움직일 조건
류제황·전장수 연구가 임상에서 이어질 경우를 가정해 보겠습니다. 병의 진행을 늦춰 수술과 입원을 줄일 수 있다면 건강보험과 환자의 직접 지출이 줄어들 수 있습니다. 걷는 기능이 유지되면 가족의 돌봄 시간과 환자의 휴업도 줄어들 여지가 있습니다. 여기부터는 연구 결과가 아니라 가능한 경제적 경로에 대한 분석입니다.
계산은 같은 기간과 같은 환자군을 기준으로 해야 합니다. 피한 진료·수술·돌봄 비용에서 새 약값, 투약 비용, 검사와 부작용 관리 비용을 빼야 순절감액이 나옵니다. 수술 시점이 뒤로 밀리는 것과 수술 자체를 피하는 것도 다릅니다. 비용을 몇 년 미뤘다는 이유만으로 그 전액이 사라졌다고 계산해서는 안 됩니다.
-
1
적격 환자 선별
반응을 예측할 지표 검증
-
2
임상 편익 입증
연골·통증·기능을 각각 평가
-
3
치료 부담 감소
수술·입원·돌봄 감소를 관찰
-
4
추가 비용 차감
약값·투약·검사·안전관리 포함
산업 구조도 이런 조건에 따라 달라집니다. 효과가 입증되면 제약사는 장기 진행 억제 치료라는 기회를 얻고, 검사·영상평가 업체는 환자 선별과 추적 수요를 얻을 수 있습니다. 반면 인공관절 기업의 수요 감소는 수술 지연이 실제로 확인될 때의 먼 시나리오입니다. 고령화로 전체 환자가 늘면 새 치료제가 등장해도 수술 건수가 함께 증가할 수 있습니다.
한국에서 후속 연구를 평가할 때는 기술이전 계약 규모보다 사람 대상 시험의 설계가 먼저입니다. 어떤 환자를 모집하는지, 통증과 기능을 함께 평가하는지, 기존 치료에 더한 이익이 있는지 살펴볼 필요가 있습니다. 이번 연구와 연결된 기업 계약이나 투자액은 확인한 자료에 없어 제시하지 않습니다. 연구진이 발견한 표적과 특정 기업의 매출을 바로 연결할 근거도 없습니다.
다음에 확인할 것은 사람의 관절입니다
류제황·전장수 교수팀은 관절이 받는 전신 신호를 치료 표적으로 구체화했습니다. 김수진·김효은 공동 제1저자가 참여한 작업의 가치는 고혈압과 관절염이 같이 나타난다는 관찰을 실험 가능한 경로로 바꾼 데 있습니다. 이제 필요한 것은 사람에게서 그 경로를 막았을 때 얻는 이익의 크기와 지속성입니다.
독자가 이번 연구에서 가져갈 메시지는 약을 바꾸라는 권유가 아닙니다. 혈압과 관절 상태를 함께 살펴볼 과학적 이유가 더 구체적으로 생겼다는 점입니다. 치료비의 변화도 연골 사진 한 장보다, 환자가 얼마나 덜 아프고 오래 움직이며 추가 치료를 피하는지에 달려 있습니다.
치료의 경제적 가치는 환자가 덜 아프고 오래 움직일 수 있다는 증거에서 시작됩니다.
출처와 참고 링크
- Science: Hypertension fuels osteoarthritis through neuroendocrine signaling
- Science 논문 초록·저자 명단 — CiteDrive 재수록
- 전남대학교 치의학전문대학원 공식 연구 발표
- 과학기술정보통신부 보도자료 — 정책브리핑
- 과학기술정보통신부 발표 요약 — KDI
- Nature 2019: The CH25H–CYP7B1–RORα axis of cholesterol metabolism regulates osteoarthritis
- WHO: Osteoarthritis
- JAMA 2019: FORWARD randomized clinical trial
A blood-pressure check and a knee scan may seem like unrelated appointments. Signals carried in the bloodstream can connect the two. That does not mean blood-pressure medication treats osteoarthritis. This is not a clinical trial in patients; the pathway was tested in animals.
Who led the study: Ryu and Chun’s team
Ryu and Chun are the co-corresponding authors. Su-Jin Kim, a postdoctoral researcher at Chonnam, and Hyo-Eun Kim are the co-first authors. The university identifies their shared role in conducting the research without assigning individual experiments to either researcher. Source: 연구진 명단
The senior researchers have a history of studying metabolic influences on cartilage. Ryu and Chun were also corresponding authors of a 2019 Nature paper on a cholesterol-metabolism pathway in osteoarthritis. The new work extends that line of inquiry to blood pressure and neuroendocrine signaling: hormones produced by the nervous system influencing distant tissues through the circulation. Source: Nature 2019 선행 연구
What hypertension adds to the wear-and-tear explanation
Vasopressin, or AVP, is a hormone involved in regulating water balance and blood pressure. AVPR1A is a receptor through which cells receive its signal. Ryu and Chun examined both the circulating signal and the cartilage cell’s readiness to respond.
The paper’s abstract reports increased AVPR1A in OA-primed cartilage cells. Exposure to hypertension-associated circulating AVP amplified breakdown signals and suppressed regulators of cartilage production. Transcriptomic profiling and gene-silencing experiments identified NR4A3 as a downstream transcriptional mediator—a protein that helps control which genes a cell activates. Source: Science 초록 재수록
The condition of the joint matters. Healthy cartilage has little of the receptor, whereas injured or aged cartilage has more. This does not justify saying that hypertension necessarily damages every healthy joint. It points to an interaction between a susceptible tissue and a systemic signal. Source: 연골 상태에 따른 차이
-
1
Circulating AVP
A hormone signal associated with hypertension
-
2
Cartilage AVPR1A
Receptor increases with injury or aging
-
3
Stronger catabolic signaling
Downstream regulation including NR4A3
-
4
Faster degeneration
Acceleration in predisposed joints
Scientifically, the question expands from how much a joint has been loaded to why certain cells react more strongly to the same hormonal message. Mechanical load and body weight remain relevant. The new work adds a molecular target that could influence the pace of degeneration.
Where human association and animal causality diverge
The work involving co-first authors Su-Jin Kim and Hyo-Eun Kim connects population observations with mouse experiments. Official accounts describe two distinct hypertensive mouse models. Observing two conditions together in people and experimentally changing a pathway in animals provide different kinds of evidence. Source: 과기정통부·KDI 연구 요약
Age, weight, activity and medication use can complicate human associations. Residual confounding can remain even after statistical adjustment. In mice, genetic deletion or pharmacological inhibition of AVPR1A protected against hypertension-driven acceleration, strengthening the case for a causal role of the target. That finding does not substitute for evidence of durable benefit in patients. Source: Science 초록의 실험 결과
Human observations
Hypertension–OA association
Finding
Limit · No proof of joint benefit from BP treatment
Mouse interventions
Protection after receptor deletion or inhibition
Finding
Limit · No direct proof of long-term human efficacy
A source limitation matters here. Publisher access was restricted, so this article cross-checks the reproduced paper abstract against official university and government releases. The full paper and supplement were not available for verification of sample sizes, dosing details or effect magnitudes; no percentage improvement or human risk multiplier is asserted.
Relcovaptan is a development lead, not a prescribing answer
Ryu’s team also reported reduced cartilage damage in animals treated with relcovaptan, an AVPR1A inhibitor. This moves the work beyond identifying a target to testing whether a compound can intervene. It does not establish relcovaptan as an approved osteoarthritis treatment or a substitute for a patient’s blood-pressure prescription. Source: 렐코밥탄 동물실험
A developer would need to establish adequate exposure in human joints and the duration of any effect. Systemic and intra-articular delivery pose different exposure and repeat-treatment questions. Long-term safety also matters in older patients taking multiple medicines. These are development requirements, not outcomes established by this paper.
One possible source of development efficiency is patient selection. If hypertension and pathway activity identify a responsive group, trials might avoid enrolling many people unlikely to benefit. Expensive or unreliable selection tests could instead add cost. Blood pressure alone is not yet a validated predictor of response.
Better cartilage images do not automatically lower costs
A useful precedent for assessing Ryu and Chun’s target is the FORWARD trial involving Marc Hochberg and researchers from Merck KGaA and EMD Serono. Its 2019 JAMA report found a cartilage-thickness effect in higher-dose sprifermin groups without significant improvement over placebo in overall symptom measures, including pain and function. This is historical evidence about a different drug, not a prediction that relcovaptan will fail. Source: JAMA FORWARD 임상
The commercial lesson is to measure cartilage preservation, pain and walking ability, and delayed surgery separately. The value proposition to payers strengthens when structural effects translate into practical benefits. Target validation in a laboratory and the clinical evidence needed to justify a treatment’s price are far apart.
WHO estimates that roughly 528 million people had osteoarthritis in 2019. This describes disease burden, not a new drug’s addressable customer base. Eligibility depends on pathway relevance, disease stage and safe use. Multiplying global prevalence by an imagined drug price would bypass the central uncertainties. Source: WHO·2019년 기준
What would change spending in Korean health care?
Consider a conditional scenario in which Ryu and Chun’s findings translate into clinical benefit. Slower progression that prevents operations and hospital stays could reduce direct spending by patients and Korea’s health insurer. Preserved mobility might also reduce family care time and work absence. These are economic inferences, not measured outcomes of the study.
A valid calculation needs the same patient group and time horizon on both sides. Net savings equal avoided medical and care costs minus drug, administration, testing and adverse-event costs. Postponing an operation is also different from avoiding it. A deferred bill cannot simply be counted as a permanently eliminated bill.
-
1
Select eligible patients
Validate predictors of response
-
2
Show clinical benefit
Assess structure, pain and function
-
3
Reduce care burden
Measure operations, admissions and care
-
4
Subtract added costs
Include drugs, delivery, tests and safety
The industrial effects would depend on those conditions. Proven benefit could create a disease-slowing treatment opportunity for pharmaceutical companies and demand for selection and monitoring services. Reduced implant demand is a more distant scenario requiring actual evidence of fewer or later operations. An aging population could still expand surgical volumes alongside a new treatment.
For follow-up development in Korea, human trial design matters before any licensing headline: who is enrolled, whether pain and function are assessed, and whether benefit is added to existing care. The reviewed sources do not establish a company deal or investment amount tied to this study. They also do not justify assigning future revenue to a particular company.
The next test is in human joints
Ryu and Chun’s team has made a systemic signal to the joint into a concrete therapeutic hypothesis. The work involving Su-Jin Kim and Hyo-Eun Kim turns a familiar association into an experimentally testable pathway. The next question is the size and durability of benefit when that pathway is blocked in people.
For readers, the message is a more specific scientific reason to consider blood pressure and joint health together, not an instruction to change medicines. Any change in care costs will depend on less pain, sustained mobility and avoided treatment—not a cartilage image alone.
The economic value of treatment begins with evidence of less pain and sustained mobility.
Sources and further reading
- Science: Hypertension fuels osteoarthritis through neuroendocrine signaling
- Science 논문 초록·저자 명단 — CiteDrive 재수록
- 전남대학교 치의학전문대학원 공식 연구 발표
- 과학기술정보통신부 보도자료 — 정책브리핑
- 과학기술정보통신부 발표 요약 — KDI
- Nature 2019: The CH25H–CYP7B1–RORα axis of cholesterol metabolism regulates osteoarthritis
- WHO: Osteoarthritis
- JAMA 2019: FORWARD randomized clinical trial
이 글은 정보 제공 목적이며, 특정 자산의 매수·매도를 권유하지 않습니다.
For information only — this is not a recommendation to buy or sell any asset.
댓글Comments 0