MedGemma 의료 AI: 흉부 X선 15.5포인트 향상, 병원 비용도 줄어들까MedGemma medical AI: a 15.5-point chest X-ray gain, but will hospital costs fall?
Google의 앤드루 셀러그렌(Andrew Sellergren)과 린 양(Lin Yang) 등이 개발한 MedGemma는 의료 AI를 만드는 출발 비용을 낮출 수 있는 공개 모델입니다. 2026년 10월 6일 Nature Medicine에 실린 논문에서 흉부 X선 평가 점수는 같은 크기의 범용 모델보다 15.5포인트 높았습니다. 병원과 의료 AI 회사가 주목할 부분은 이 점수 자체보다, 적은 데이터로 필요한 기능을 만들 수 있느냐는 데 있습니다. 출처: Nature Medicine · 2026-10-06
MedGemma, developed by Google researchers including Andrew Sellergren and Lin Yang, could lower the cost of getting a medical AI project started. Their October 6, 2026 Nature Medicine paper reports a 15.5-point gain over a similarly sized general model on one chest X-ray benchmark. For hospitals and developers, the practical question is whether that stronger starting point reduces the work needed to build a useful application. Source: Nature Medicine · 2026-10-06
먼저 날짜부터 구분해야 합니다. Google은 2025년부터 MedGemma를 공개했고, 같은 해 7월에는 MedSigLIP과 멀티모달 27B 모델을 소개했습니다. 이번 소식은 모델의 첫 출시가 아니라 학술지 최종 논문 게재입니다. 이 글도 해당 논문을 기준으로 읽으며, 후속 MedGemma 1.5의 기능이나 성능을 섞지 않습니다. 출처: Google Research · 2025-07-09
MedGemma를 만든 Google 연구진은 누구인가
셀러그렌과 양은 사하르 카젬자데(Sahar Kazemzadeh) 등과 함께 연구 설계와 기술 구현에 참여했습니다. 교신저자인 데이비드 F. 스타이너(David F. Steiner)는 임상 지도와 데이터 확보에도 기여했습니다. Google Research와 Google DeepMind가 협력한 연구로, 알고리즘을 만드는 사람과 의료 결과를 해석하는 사람이 함께 참여한 구성입니다. 출처: 논문 저자 기여 / Author contributions
양이 제1저자로, 셀러그렌이 공동저자로 참여한 2024년 Med-Gemini 연구는 영상과 의료 언어를 함께 다루는 선행 작업입니다. 이번 연구를 이해하는 데도 이 흐름이 도움이 됩니다. Med-Gemini가 영상과 의료 언어를 함께 읽는 능력을 보여 준 연구였다면, MedGemma는 그 능력을 외부 개발자가 내려받아 자기 문제에 맞게 고쳐 쓸 수 있게 만든 쪽에 가깝습니다. 출처: Med-Gemini · 2024 preprint
한 가지는 감안해야 합니다. 이 연구는 Alphabet 계열의 지원을 받았고, 논문은 저자 다수가 Google 현직·전직 직원이라는 이해관계를 공개합니다. 제품 개발팀의 벤치마크는 출발 근거로 읽되, 다른 병원에서 같은 결과가 나오는지는 별도로 확인해야 합니다. 출처: 논문 연구비·이해관계 / Disclosures
MedGemma는 범용 챗봇과 어디서 달라질까
MedGemma는 Gemma 3를 바탕으로 의료 영상과 글을 추가로 학습했습니다. 비전-언어 모델은 이미지를 입력받고 그 내용에 관한 질문에 글로 답하는 AI입니다. 파운데이션 모델이라는 말은 여러 업무를 개발할 때 공통 출발점으로 쓸 수 있다는 뜻입니다. 특정 질병 하나만 찾도록 완성한 프로그램과는 쓰임새가 다릅니다. 출처: Google · MedGemma 1 model card
여기서 MedSigLIP은 영상 인코더 역할을 합니다. 인코더는 영상의 특징을 컴퓨터가 비교할 수 있는 숫자로 바꿉니다. 비슷한 영상을 찾거나 정해진 항목으로 분류하는 업무라면 긴 설명문을 생성하는 기능이 꼭 필요하지 않습니다. Google도 이런 작업에는 MedSigLIP을, 설명문이나 질의응답이 필요한 작업에는 MedGemma를 구분해 안내합니다. 출처: Google · 모델별 용도 / Model use cases
MedGemma
질문에 대한 글·설명문
출력
개발 예 · 보고서 초안·영상 질의응답
MedSigLIP
비교 가능한 영상·글의 특징
출력
개발 예 · 유사 영상 검색·분류
이 차이는 제품 설계에서 중요합니다. 예를 들어 연구용 영상 보관함에서 비슷한 사례를 찾는 기능이라면, 매번 긴 답변을 만드는 시스템보다 검색에 필요한 부분만 실행하는 편이 합리적일 수 있습니다. 다만 이것은 설계상의 비용 절감 가능성입니다. 실제 서버비는 영상 크기, 처리량, 응답 속도, 장비 사용률을 넣어 비교해야 합니다.
15.5포인트 향상은 진단 정확도와 다릅니다
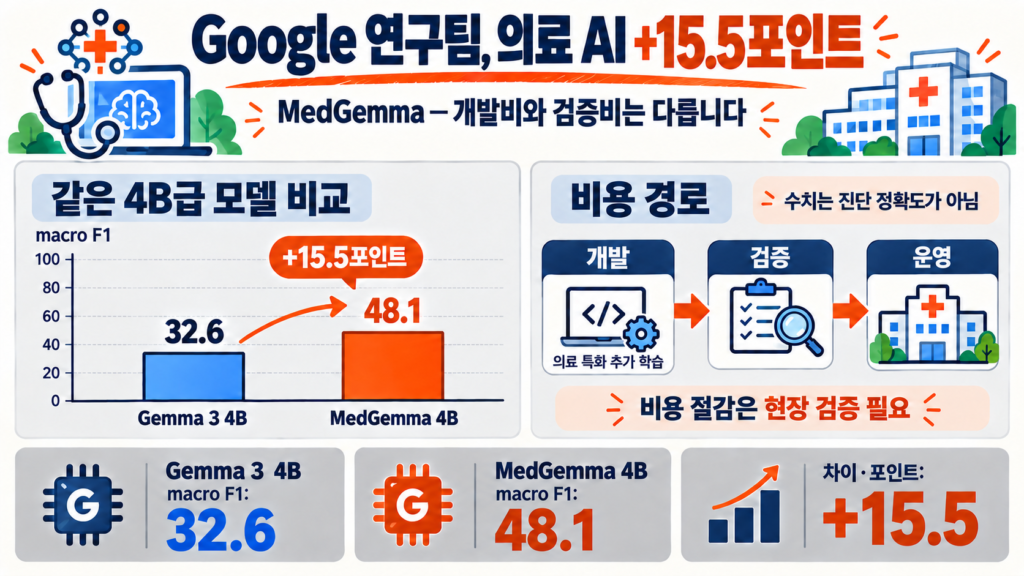
논문의 CheXpert 평가에서 Gemma 3 4B는 32.6, MedGemma 4B는 48.1을 기록했습니다. 둘 다 4B급 모델이며, 이 평가의 지표는 다섯 가지 흉부 소견에 대한 macro F1입니다. 질환별로 놓친 사례와 잘못 잡아낸 사례를 함께 반영한 F1 점수를 구한 뒤, 각 질환에 같은 비중을 주어 평균한 값입니다. 출처: Nature Medicine · Table 3
Nature Medicine 표 3. 다섯 소견, 0–100 척도, zero-shot 생성형 분류. +15.5포인트이며 진단 정확도나 비용 절감률이 아닙니다.
솔직히 이 대목이 가장 오해받기 쉽습니다. 이 결과를 “환자 100명 중 48명을 정확히 진단했다”로 읽으면 안 됩니다. 두 점수의 차이는 15.5포인트이며, 진단 정확도 15.5% 상승이나 의료비 15.5% 절감도 뜻하지 않습니다. 논문에서 이 데이터는 모델 개발에 쓰이지 않은 출처로 분류되지만, 한국 병원의 환자와 촬영 장비에서도 그대로 유지된다는 보장은 아닙니다. 출처: Nature Medicine · Tables 1, 3
경제성 평가에서는 점수 다음의 업무를 봐야 합니다. 의사가 결과를 확인하는 시간이 줄었는지, 잘못된 경고 때문에 추가 검토가 늘었는지, 중요한 이상을 놓치지 않았는지가 필요합니다. 높은 평균 점수를 얻어도 사람이 매번 오래 고쳐야 한다면 병원의 처리량은 거의 늘지 않을 수 있습니다.
적은 데이터가 바꾸는 것은 개발 예산입니다
양과 동료들은 과제별 데이터를 10%만 쓰는 추가 학습 조건에서도 의료 특화 모델의 이점을 관찰했습니다. 추가 학습, 즉 파인튜닝은 이미 학습된 AI를 특정 업무의 예시로 더 훈련하는 과정입니다. 이 결과는 적은 예시로 시작하는 개발팀에 유리한 출발점이 될 수 있다는 근거입니다. 라벨링 비용을 90% 줄였다는 실험은 아닙니다. 출처: Nature Medicine · Extended Data Fig. 2 / Methods
라벨링은 영상에 정답을 붙이는 일입니다. 의료 영상에서는 전문가가 병변을 확인하고, 의견이 다르면 다시 판정해야 합니다. 이미 의료 특징을 배운 모델로 같은 목표 성능에 더 빨리 도달한다면 이런 예시를 만드는 비용과 반복 실험비를 줄일 여지가 있습니다. 여기부터는 논문의 실측 비용이 아닌 경제적 추론입니다.
그러나 개발용 예시를 적게 쓴다는 사실과 제품을 검증할 자료가 적어도 된다는 주장은 별개입니다. 드문 질환, 다른 장비, 다른 연령대에서의 오류를 찾으려면 대표성 있는 평가 자료가 필요합니다. 저렴하게 시제품을 만든 회사가 검증비까지 덜 들 것이라고 예산을 잡으면, 출시 직전에 자금이 부족해질 수 있습니다.
비용의 이동 경로는 이렇습니다. 공개된 모델로 기초 개발을 시작하고, 병원 자료로 필요한 기능을 조정한 뒤, 현장 검증과 기존 시스템 연결에 돈을 씁니다. 운영에 들어간 후에도 오류를 추적하고 버전을 관리해야 합니다. 절감액은 앞부분에서 줄인 학습·검토비에서 새로 발생한 서버·연동·검증·운영비를 빼고 계산해야 합니다.
-
1
공개 모델 활용
기초 개발 반복 부담 감소 가능
-
2
업무별 추가 학습
라벨·데이터 정리·성능 비교
-
3
병원 검증·연동
오류 확인·기존 시스템 연결
-
4
운영·변경 관리
서버·감시·업데이트 재검증
병원·임상시험에서 돈이 줄어들려면
이번 연구를 실제 진료의 수익성으로 연결하려면, 먼저 한 가지 업무를 좁혀 검증해야 합니다. 판독문 초안을 만드는 경우라면 초안을 쓰는 시간만 재면 부족합니다. 의사가 확인하고 수정해 최종 서명할 때까지 걸린 시간을 봐야 합니다. 그 시간이 줄고 오류 부담도 늘지 않아야 생산성 향상으로 이어집니다.
시간이 절약되어도 진료비가 바로 내려가지는 않습니다. 인력이 부족한 병원은 절약한 시간을 대기 환자나 어려운 사례에 쓸 수 있습니다. 병원은 같은 인력으로 더 많은 업무를 처리하고 환자는 덜 기다릴 수 있지만, 그 이익이 요금 인하로 전달될지는 병원의 계약과 지불 구조에 달려 있습니다. 인건비 절감과 서비스 공급 확대는 서로 다른 결과입니다.
임상시험에서는 조건에 맞을 가능성이 있는 기록을 먼저 찾아 주거나 연구용 영상을 분류하는 보조 기능을 생각해 볼 수 있습니다. 논문이 입증한 결과가 아니라, 영상·언어 기반 모델을 활용한 응용 전망입니다. 후보 목록을 사람이 검토해야 하며, 빠진 후보와 잘못 포함된 후보가 얼마나 되는지도 확인해야 합니다. 이번 논문은 시험 대상자 모집률, 시험기간, 임상시험 비용 감소를 입증하지 않았습니다.
산업계의 움직임은 이미 있습니다. Google은 2025년 발표에서 미국 DeepHealth 개발자들이 MedSigLIP을 흉부 영상 선별과 결절 탐색에 활용할 가능성을 검토한다고 소개했습니다. 다만 개발사 측이 소개한 탐색 사례입니다. 이 설명만으로 유료 계약, 규제 승인, 매출 증가까지 확인할 수는 없습니다. 출처: Google Research · 개발 사례 / Developer examples
공개 모델이 보급되면 특정 영상 AI의 기본 기능을 처음 만드는 비용은 경쟁 압력을 받을 수 있습니다. 반대로 병원 자료를 정리하고, 성능을 독립적으로 검증하고, 운영 중 오류를 관리하는 서비스에는 새 수요가 생길 수 있습니다. 기존 의료 AI 기업도 같은 기반을 활용할 수 있으므로, 이것이 곧 기존 기업의 퇴장을 뜻하지는 않습니다. 차별화의 기준이 모델 보유 자체에서 검증된 업무 성과로 옮겨갈 가능성이 있습니다.
한국에서는 연동과 책임까지 제품에 넣어야 합니다
MedGemma를 내려받아 쓸 수 있다는 점은 병원이 사용할 버전을 고정하고 내부 환경에서 운영하는 데 유리할 수 있습니다. 하지만 “공개”는 아무 조건 없이 쓴다는 뜻이 아닙니다. HAI-DEF 약관은 사용·재배포 조건을 두고, 해당되는 규제 승인을 확보하도록 하며, 출력과 그 사용에 대한 책임도 명시합니다. 모델 사용 허락과 의료제품 허가는 서로 다른 문제입니다. 출처: Google · HAI-DEF Terms of Use
한국에서는 디지털의료제품법이 2025년 1월 24일부터 시행됐습니다. 식약처는 디지털의료기기 품질관리 안내에서 AI·머신러닝 기능 추가 등의 변경에 대한 심사도 설명합니다. 어떤 절차가 필요한지는 완성된 제품의 목적과 변경 내용에 따라 확인해야 합니다. 논문 게재나 모델 공개만으로 그 절차가 끝나는 것은 아닙니다. 출처: 식약처 · 디지털의료기기 GMP / MFDS
병원 입장에서 더 구체적인 문제는 연결입니다. 의료영상저장전송시스템, 즉 PACS에서 영상을 가져오고, 전자의무기록과 환자 정보를 정확히 연결하고, 접근 권한과 변경 이력을 남겨야 합니다. 한국어 판독 표현과 병원별 촬영 방식에서도 결과를 점검해야 합니다. 이는 이번 논문이 한국 시장의 효과를 입증했다는 주장이 아니라, 도입 비용을 계산할 때 빠뜨리지 말아야 할 항목입니다.
병원정보시스템 업체에는 기존 화면 안에서 결과를 보여 주고 검토 기록을 남기는 기능이 사업 기회가 될 수 있습니다. 의료 AI 업체에는 자체 자료와 현장 평가 경험이 중요해집니다. 모델이 답을 내놓는 데 성공했다는 사실보다, 누가 오류를 발견하고 수정하며 업데이트 비용을 부담할지까지 정한 제품이 구매자에게 더 설득력 있을 것입니다.
셀러그렌과 양의 연구가 보여 준 가치는 의료 AI 개발을 더 나은 출발점에서 시작할 수 있다는 데 있습니다. 앞으로 확인할 숫자는 병원별 오류율, 최종 검토시간, 건당 전체 운영비입니다. 이 세 지표가 함께 좋아져야 벤치마크의 향상이 의료 서비스의 경제적 가치로 이어집니다. 이 글은 연구 해설이며, 특정 기업에 대한 투자 권유나 의료적 판단 근거가 아닙니다.
의료 AI의 경제적 가치는 병원에서 확인한 오류율, 검토시간, 전체 운영비로 평가해야 합니다.
출처와 참고 링크
- Nature Medicine (2026-10-06): An open vision-language model for diverse medical applications
- Nature Medicine 최종 논문 PDF: 표 3·Methods·저자 기여
- Google Research (2025-07-09): MedGemma 공개와 개발 사례
- Google: MedGemma 1 model card
- Google: Health AI Developer Foundations Terms of Use
- 식약처: 디지털의료제품 법령 시행에 따른 업무 안내
- 식약처: 디지털의료기기 GMP 안내
- Yang et al. (2024): Advancing Multimodal Medical Capabilities of Gemini
- MedGemma Technical Report v3 (2025-07-12)
The publication date is not the launch date. Google began releasing MedGemma in 2025 and introduced MedSigLIP and the multimodal 27B model that July. This is a journal publication, not a first product launch. The analysis below concerns the models in that paper, without importing capabilities or results from the later MedGemma 1.5 release. Source: Google Research · 2025-07-09
Who built MedGemma at Google
Sellergren, Yang and Sahar Kazemzadeh contributed to study design and technical implementation. Corresponding author David F. Steiner also contributed clinical guidance and data acquisition. The collaboration brought Google Research and Google DeepMind together, combining model development with clinical expertise. Source: 논문 저자 기여 / Author contributions
Yang was first author and Sellergren a coauthor of the 2024 Med-Gemini work on multimodal medicine. If Med-Gemini showed that a model could read images and medical language together, MedGemma is closer to packaging that ability so outside developers can download it and adapt it to their own problems. Source: Med-Gemini · 2024 preprint
The paper discloses Alphabet funding and that most authors are current or former Google employees. Its benchmarks are evidence about a development platform; replication in other hospitals remains a separate question. Source: 논문 연구비·이해관계 / Disclosures
How MedGemma differs from a general chatbot
The team adapted Gemma 3 with medical images and text. A vision-language model takes an image and can answer questions about it in words. A foundation model provides a reusable starting point for multiple applications. It is different from a finished program designed to detect one specific disease. Source: Google · MedGemma 1 model card
MedSigLIP is an image encoder: it converts visual features into numbers that software can compare. Searching for similar images or classifying them does not necessarily require generating a paragraph. Google distinguishes MedSigLIP for those structured tasks from MedGemma for tasks that need generated text. Source: Google · 모델별 용도 / Model use cases
MedGemma
Generated answers and text
Output
Example · Draft reports and image Q&A
MedSigLIP
Image and text representations
Output
Example · Similarity search and classification
That distinction matters when designing a product. A research image archive may need similarity search without a generated explanation for every result. Running only the components needed for that task could be more economical. This is an engineering inference, however: actual server costs depend on image size, workload, latency and hardware utilization.
What the 15.5-point improvement measures
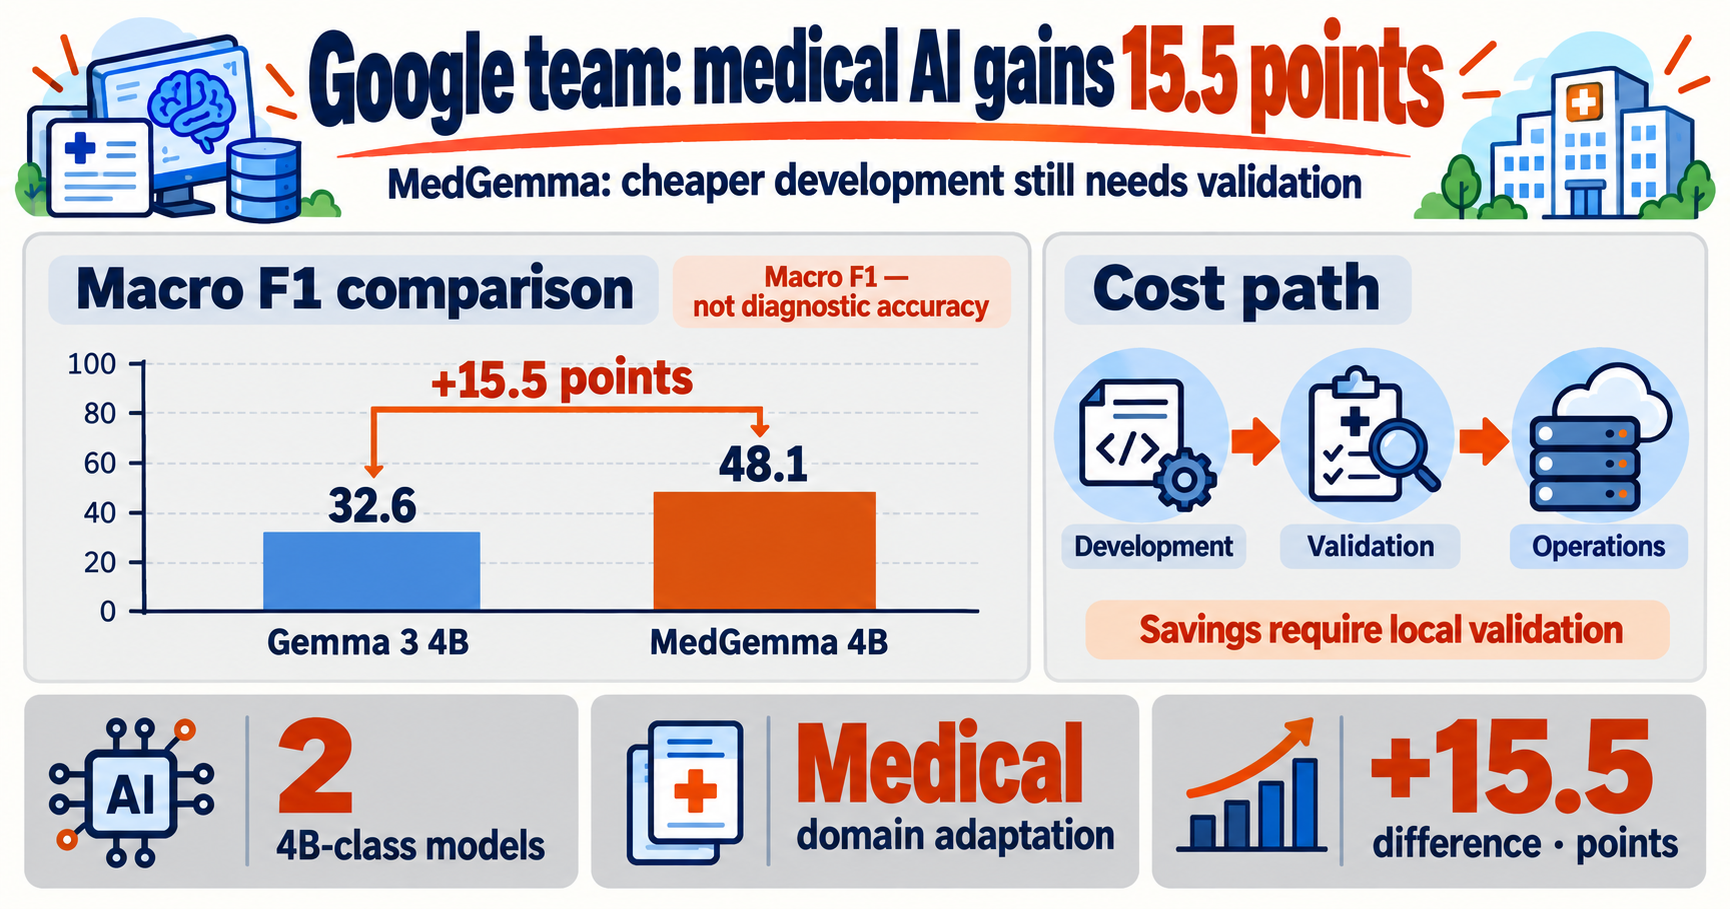
On CheXpert, Gemma 3 4B scored 32.6 and MedGemma 4B scored 48.1. Both are 4B-class models. The metric is macro F1 across five chest findings: it balances missed findings and false detections within each class, then gives each class equal weight in the average. Source: Nature Medicine · Table 3
Nature Medicine Table 3. Five findings, 0–100 scale, zero-shot generative classification. +15.5 points; not diagnostic accuracy or cost savings.
This is the easiest part to misread. A score of 48.1 does not mean that 48 out of 100 patients were correctly diagnosed. The difference is 15.5 points, not a measured 15.5% improvement in diagnostic accuracy or a 15.5% saving in medical spending. The study treats this data source as outside model development, which still does not establish performance in Korean hospitals. Source: Nature Medicine · Tables 1, 3
The economic test comes after the benchmark. Does review take less time? Do false alarms create additional work? Are important abnormalities still detected? A better average score can produce little additional capacity if a clinician must spend substantial time correcting every output.
Less task data could change the development budget
Yang and colleagues found an advantage for the medical model in fine-tuning experiments using only 10% of the available task data. Fine-tuning means giving an already trained model additional examples for a particular job. This supports a better starting point when examples are scarce; it is not evidence of a 90% reduction in labeling costs. Source: Nature Medicine · Extended Data Fig. 2 / Methods
Labeling means establishing the answers an AI should learn from. Medical images may require specialist review and adjudication of disagreements. If a medically trained model reaches the same target performance with fewer examples or fewer experiments, some of that work could be avoided. This is an economic inference, not a measured cost outcome in the paper.
Using fewer training examples is separate from needing fewer validation cases. Rare conditions, different scanners and different age groups still require representative evaluation. A company that budgets for cheap validation simply because its prototype was cheap could run short of money before launch.
The spending moves through a sequence: start with the released model, adapt it to the intended task, validate and connect it to hospital systems, then monitor errors and manage versions. Net savings equal avoided training and review work minus additional compute, integration, validation and operating costs.
-
1
Reuse the model
Potentially avoid repeated foundational work
-
2
Adapt to the task
Labels, data preparation and evaluation
-
3
Validate and integrate
Measure errors and connect existing systems
-
4
Operate and maintain
Compute, monitoring and update validation
What would make hospitals and clinical trials cheaper?
To translate this study into hospital economics, the first step is a narrowly defined workflow. For a reporting assistant, timing draft generation alone is insufficient. The relevant measure includes clinician review, correction and final sign-off. Productivity improves only if the full task gets shorter without adding an unacceptable error burden.
Saved time does not automatically lower the patient bill. A hospital short of staff may use the released capacity for waiting patients or difficult cases. It could do more work with its existing workforce, while patients wait less. Whether those gains become lower prices depends on contracts and payment arrangements. Lower labor spending and expanded service capacity are different outcomes.
For clinical trials, a possible application is to retrieve records that may meet eligibility criteria or classify research images. That is a prospective use of an image-and-language foundation model, not a result the paper demonstrated. People would still check the shortlist, including missed candidates and unsuitable inclusions. The paper does not establish improved recruitment, shorter trials or reduced trial costs.
There is an industry signal: in its July 2025 announcement, Google said developers at US-based DeepHealth were exploring MedSigLIP for chest X-ray triage and nodule detection. This is a vendor-reported exploration. It does not, by itself, establish paid contracts, regulatory authorization or additional revenue. Source: Google Research · 개발 사례 / Developer examples
Wider access could put price pressure on the initial development of basic imaging AI features. It could also create demand for data preparation, independent validation and ongoing error monitoring. Existing medical AI companies can use the same foundation, so displacement is not inevitable. Competitive advantage may increasingly depend on verified workflow results rather than possession of a model alone.
In Korea, integration and accountability are part of the product
Being able to download the model can help a hospital fix a version and operate it in its own environment. But open access does not mean unrestricted use. HAI-DEF terms impose conditions on use and redistribution, require applicable regulatory authorization, and assign responsibility for outputs and their uses. A model license is separate from medical product authorization. Source: Google · HAI-DEF Terms of Use
Korea’s Digital Medical Products Act took effect on January 24, 2025. MFDS guidance on digital medical device quality management also describes change reviews, including changes such as adding AI or machine-learning functions. The pathway for a particular product depends on its intended purpose and the proposed changes. Publication of a paper does not complete that process. Source: 식약처 · 디지털의료기기 GMP / MFDS
For a hospital, integration is concrete work: retrieve images from its picture archiving and communication system, or PACS; link them correctly with electronic records; and preserve access controls and change histories. Korean reporting language and local imaging practices also need evaluation. These are deployment considerations, not outcomes established for Korea by this study.
Hospital software vendors could build services that display results within existing interfaces and preserve review records. Medical AI companies could differentiate through local data and evaluation experience. A buyer needs more than a working model: the product must also specify who detects errors, corrects them and pays for updates.
Sellergren and Yang’s work offers a stronger starting point for medical AI development. The next numbers to watch are local error rates, total review time and all-in cost per completed task. Improvement across those measures is what would turn a benchmark result into economic value for healthcare. This article explains research; it is not investment advice or a basis for medical decisions.
Medical AI economics must be measured through local error rates, review time and total operating costs.
Sources and further reading
- Nature Medicine (2026-10-06): An open vision-language model for diverse medical applications
- Nature Medicine 최종 논문 PDF: 표 3·Methods·저자 기여
- Google Research (2025-07-09): MedGemma 공개와 개발 사례
- Google: MedGemma 1 model card
- Google: Health AI Developer Foundations Terms of Use
- 식약처: 디지털의료제품 법령 시행에 따른 업무 안내
- 식약처: 디지털의료기기 GMP 안내
- Yang et al. (2024): Advancing Multimodal Medical Capabilities of Gemini
- MedGemma Technical Report v3 (2025-07-12)
이 글은 정보 제공 목적이며, 특정 자산의 매수·매도를 권유하지 않습니다.
For information only — this is not a recommendation to buy or sell any asset.
댓글Comments 0